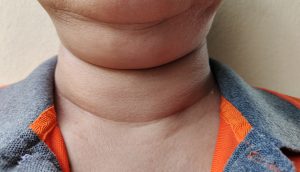
Head and Neck Lymphedema: What Makes It Different?
Introduction
Lymphedema is often associated with swollen arms or legs. But when lymphatic dysfunction affects the head and neck, the presentation can differ—and the consequences can extend well beyond visible swelling.
Head and neck lymphedema is most commonly associated with cancer treatment, particularly surgery and radiation for head and neck cancers. It can also develop after trauma, infection, or other conditions that disrupt lymphatic drainage.
For clinicians, treating this population requires more than simply applying familiar lymphedema techniques to a different body region. The anatomy, symptoms, functional consequences, and patient experience all require a more specialized approach.
The Anatomy Is Complex
The head and neck contain an extensive network of lymphatic vessels and nodes. Drainage pathways are highly interconnected, and surgery or radiation can disrupt multiple routes at once.
Unlike an extremity, the head and neck have relatively little space for fluid accumulation before swelling affects important structures.
The lymphatic pathways of the face, scalp, neck, and upper chest are closely related. Changes in one region can affect another, so assess the entire area rather than focusing only on where swelling is most obvious.
For example, a patient may present with facial fullness while the primary restriction or tissue change is occurring elsewhere along the drainage pathway.
Swelling Isn’t Always Obvious
One of the most important differences in head and neck lymphedema is that visible swelling may not tell the whole story.
Patients may report:
- A feeling of fullness or tightness in the face or neck
- Difficulty turning the head
- Changes in facial contours
- Heaviness around the eyes
- Tightness around the jaw or mouth
- A sensation of pressure in the neck
- Changes in swallowing or speech
- Skin or tissue that feels firm or less mobile
Some patients have relatively subtle external swelling but significant tissue changes or functional complaints.
This makes patient-reported symptoms particularly valuable during assessment.
The Inside of the Mouth Matters, Too
Head and neck lymphedema can involve external and internal structures.
Edema may affect the tongue, floor of the mouth, lips, pharynx, or other tissues of the oral cavity and throat.
Internal edema may not be visible during a routine external assessment, yet it can have important functional consequences.
Depending on the location and severity, patients may experience changes in swallowing, speech, breathing, or oral function.
This is one reason head and neck lymphedema often requires collaboration among multiple healthcare professionals. A therapist may identify changes that warrant communication with the patient’s oncology, speech-language pathology, medical, or other specialty team.
Radiation Changes the Tissue
Many patients with head and neck lymphedema have a history of radiation therapy.
Radiation can contribute to fibrosis, reduced tissue mobility, skin changes, and altered lymphatic function. These changes can make the tissue feel very different from uncomplicated fluid accumulation.
A clinician may encounter areas that feel:
- Firm
- Thickened
- Fibrotic
- Adherent
- Less mobile
- Sensitive or painful
This creates an important clinical distinction: not every change in tissue size represents the same thing.
A patient’s presentation may reflect a combination of fluid accumulation, fibrosis, tissue remodeling, scar formation, and other treatment-related changes.
Function Can Be More Important Than Appearance
With limb lymphedema, changes in circumference or volume can provide useful information.
With head and neck lymphedema, however, function may be an equally important—or sometimes more meaningful—part of the assessment.
Consider asking:
Has swallowing changed?
Does the neck feel tighter when turning the head?
Does facial swelling change throughout the day?
Is speaking or eating more difficult?
Does the patient feel pressure or fullness in the throat?
Has scar tissue changed how the skin or underlying tissue moves?
These questions can reveal problems that a visual inspection alone may miss.
Assessment Requires a Broader View
A head and neck lymphedema assessment should consider more than the location of visible edema.
Important areas to evaluate may include:
- Face and facial symmetry
- Chin and submental region
- Anterior and lateral neck
- Posterior neck
- Supraclavicular region
- Scars and surgical sites
- Tissue mobility
- Skin integrity
- Fibrotic changes
- Range of motion
- Patient-reported symptoms
- Functional changes
The patient’s cancer history is also critical.
The type and location of cancer, surgical procedures, lymph node dissection, radiation fields, reconstruction, and other treatments can all influence the presentation.
Treatment Isn’t Just “Drain the Face”
Because head and neck lymphatic drainage is anatomically complex, treatment requires thoughtful sequencing.
The clinician needs to understand available lymphatic pathways and identify areas that can receive and transport fluid.
Treatment may include manual lymphatic techniques, compression when appropriate, exercise and movement, skin care, positioning, and self-management strategies.
However, the treatment plan should be individualized.
A patient several months after radiation with significant fibrosis may have very different needs from a patient with relatively recent postoperative edema.
Likewise, a patient with primarily external swelling may require a different approach from someone experiencing substantial internal symptoms.
Compression Can Be Challenging
Compression is another area where head and neck lymphedema differs from extremity management.
Traditional compression garments designed for arms and legs clearly do not apply to the head and neck. Specialized facial and cervical compression options may be used for appropriate patients, but you must consider comfort, fit, tissue sensitivity, scar location, and functional needs.
A compression strategy that interferes with swallowing, breathing, speech, or sleep is unlikely to be successful.
Patient tolerance matters.
The Psychological Impact Is Significant
The face and neck are highly visible areas of the body.
Even relatively mild swelling can change facial appearance and affect how a person feels about their body after cancer treatment.
Patients may already be coping with surgical scars, hair loss, changes in skin, altered facial structures, or other consequences of treatment.
For some, lymphedema becomes another visible reminder of cancer.
That means education and communication are important parts of care. Clinicians should acknowledge the patient’s concerns about appearance without reducing the condition to a cosmetic problem.
The swelling may affect identity, confidence, social interaction, and quality of life.
When Referral and Collaboration Matter
Head and neck lymphedema can involve structures and symptoms that extend beyond the scope of a lymphatic therapist’s assessment.
Changes in swallowing, voice, airway symptoms, unexplained pain, rapidly changing swelling, signs of infection, or other concerning symptoms may require medical evaluation.
A collaborative approach can be especially valuable.
Depending on the patient’s needs, care may involve oncology, physical or occupational therapy, speech-language pathology, dentistry, nutrition, medical specialists, and other professionals.
The goal is not simply to reduce swelling. It is to support function and quality of life while addressing the broader consequences of treatment.
What Makes Head and Neck Lymphedema Different?
The biggest difference may be that we cannot always judge the clinical significance of swelling by what we see externally.
A patient can have relatively subtle facial swelling and significant functional complaints. Another patient may have obvious external edema with little functional limitation.
The anatomy is complex. Treatment-related tissue changes can be substantial. Internal edema may be difficult to observe. Symptoms involving swallowing, speech, movement, and breathing can make assessment especially important.
For clinicians, this means looking beyond circumference and appearance.
Where is the swelling?
What tissues have changed?
How mobile is the skin?
What treatments has the patient received?
What symptoms are they reporting?
What functions have changed?
Those questions can help transform a general assessment of “swelling” into a more clinically meaningful understanding of the patient’s condition.
The Takeaway
Head and neck lymphedema requires clinicians to think differently.
It is not simply limb lymphedema in a different location. The anatomy differs, the functional consequences can differ, and treatment-related tissue changes can dramatically influence presentation.
For therapists working with cancer survivors, developing a strong understanding of head and neck lymphatic anatomy, assessment, fibrosis, treatment sequencing, and interdisciplinary care can make a meaningful difference.
Sometimes the most important finding isn’t the swelling we can see.
It’s the change the patient can feel.

Interested in taking an ACOLS Course? The Academy of Lymphatic Studies offers certification courses in lymphedema management and manual lymphatic drainage. CEU’s are available for nurses in select states!
For more information, course listings, and to register for an upcoming course, Click Here!